

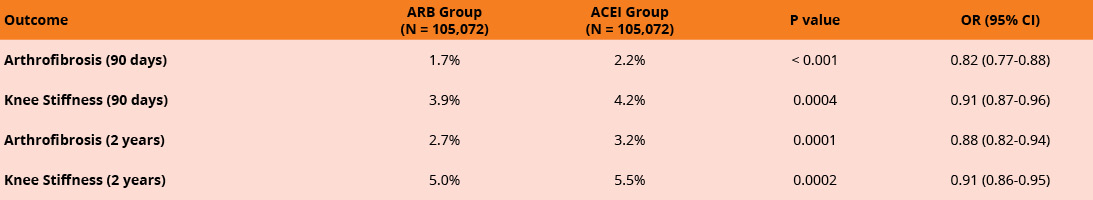
Table 1: Incidence of arthrofibrosis and knee stiffness at 90 days and 2 years Comparison of arthrofibrosis and knee stiffness rates among propensity score-matched patients receiving angiotensin II receptor blockers (ARBs) or angiotensin-converting enzyme (ACE) inhibitors during the perioperative period. ARBs were associated with lower rates of both outcomes at 90 days and two years after total knee arthroplasty.
Source: Adapted from Angiotensin Receptor Blockers (ARBs) Outperform Angiotensin-Converting Enzyme (ACE) Inhibitors in Preventing Arthrofibrosis After Knee Arthroplasty Paper 014 presented at the AAOS Annual Meeting; March 2-6, 2026; New Orleans.
Published 10/20/2026
|
Theresa Witham
At a Glance
- Perioperative ARB use was associated with lower rates of arthrofibrosis after total knee arthroplasty.
- ACE inhibitors did not demonstrate the same protective association.
- Randomized trials are needed to determine whether the relationship is causal.
Estimated read time: 2 minutes
A study at the AAOS 2026 Annual Meeting presented findings on the use of angiotensin-converting enzyme inhibitors (ACEis) and angiotensin II receptor blockers (ARBs) to lower the risk of arthrofibrosis following total knee arthroplasty (TKA).
“Arthrofibrosis is a frequent complication following total knee arthroplasty, causing joint stiffness and reduced range of motion, which often necessitates interventions such as manipulation under anesthesia (MUA) or lysis of adhesions (LOA),” stated the study’s authors. “The condition is driven by excessive fibroblast activation and inflammation; however, effective preventive treatments are currently lacking.”
Recent interest has emerged around the role of the renin-angiotensin-aldosterone system (RAAS) in modulating fibrosis. Both ACEis and ARBs have demonstrated antifibrotic effects across various organ systems. Despite their widespread use for cardiovascular and renal indications, their potential protective effects against postoperative fibrosis in orthopaedic surgery remain understudied.
In this study, researchers analyzed the outcomes of patients who received either ACEis or ARBs around the time of surgery, comparing them to patients who were not on either medication. The researchers then performed subgroup analyses separating ACEi users and ARB users to look for differences between the two drug classes. Finally, researchers directly compared outcomes between patients who received ACEis versus those who received ARBs to explore potential class-specific effects. They conducted a retrospective cohort study using the TriNetX Research Network, a large, federated database of deidentified electronic health records from healthcare organizations across the United States. Adult patients who underwent primary TKA between 2005 and 2025 were identified using standardized ICD-10 and Current Procedural Terminology codes. Medication exposure was defined as active prescription of either an ACE inhibitor or an ARB during the perioperative period, which was defined as within three months before or after the date of surgery.
The researchers constructed four primary comparisons: (1) patients prescribed either an ACEi or ARB versus patients not prescribed either, (2) ACEi users versus non-ACEi users, (3) ARB users versus non-ARB users, and (4) ACEi users versus ARB users. For each comparison, cohorts were matched 1:1 using propensity score matching based on age, sex, race, BMI, comorbidities (including diabetes and hypertension), and concurrent medications. Short-term outcomes (assessed at 90 days) and long-term outcomes (assessed at two years) included clinically coded diagnoses of persistent knee stiffness and arthrofibrosis, which was defined as receipt of MUA or LOA.
Related Content
- Do Newer-Generation Total Knee Arthroplasty Systems Improve Implant Survivorship Rates? (AAOS Now)
- Medial unicompartmental arthroplasty of the knee (JAAOS®)
- Cemented Versus Noncemented Total Knee Arthroplasty Outcomes (JAAOS®)
“After matching, 105,072 patients were included in the short-term analysis, and 75,277 patients were included in the long-term analysis,” the researchers stated. “ACEi/ARB users had lower rates of knee stiffness and arthrofibrosis compared to nonusers at both time points (P < 0.001). Subgroup analysis revealed that ARB users consistently had lower rates of both conditions, whereas ACEi users did not show significant differences. A direct comparison between ARBs and ACEis revealed that ARBs were more effective in reducing arthrofibrosis at both time points (P < 0.001 and P = 0.005).” (Table 1)
The study’s retrospective design and dependence on electronic health records introduce potential bias, and unmeasured factors may still have influenced the link between ACEi/ARB use and postoperative outcomes. Medication adherence and dosing were not evaluated, limiting interpretation of drug effectiveness. Arthrofibrosis was identified through diagnostic codes and procedures like MUA or LOA, which may miss milder cases. Because the research is observational, it cannot establish causality, reinforcing the need for randomized trials to verify whether ARBs provide a protective benefit.
Despite the limitations, this study demonstrates a consistent association between perioperative ARB use and a reduced risk of arthrofibrosis and joint stiffness, both in the short and long term. Clinicians may consider favoring ARBs in the perioperative period for high-risk patients undergoing TKA.
The authors of “Angiotensin Receptor Blockers (ARBs) Outperform Angiotensin-Converting Enzyme (ACE) Inhibitors in Preventing Arthrofibrosis After Knee Arthroplasty” are Alireza Mirahmadi, MD; Jad Lawand, BS; Kaveh Momenzadeh, MD; Jeremiah Alexander, MD; and Ara Nazarian, PhD.
Theresa Witham is managing editor of AAOS Now.